


Central Disorders of Hypersomnolence
Evaluation for persistent excessive daytime sleepiness despite adequate nighttime rest.
- Assessment of narcolepsy, idiopathic hypersomnia, and related conditions.
- Care for impaired alertness, concentration, driving, and daily function.
- Personalized diagnosis and treatment planning.
- Same-day or next-day appointments often available.


Important Medical Notice
The information provided below and throughout this website is presented for general educational purposes only and does NOT constitute professional medical advice. This information is NOT a substitute for professional medical advice and NO material on this site is intended to be a substitute for professional medical advice. Always seek the guidance of your doctor or other qualified health professional with any questions you may have regarding a health or a medical condition. Never disregard the advice of a medical professional or delay in seeking it because of something you have read on this website.
Understanding Daytime Sleepiness
What Are Central Disorders of Hypersomnolence?
Central disorders of hypersomnolence are a category of sleep conditions defined by excessive daytime sleepiness (EDS) that cannot be attributed to disturbed or insufficient nocturnal sleep, another sleep disorder, or an underlying medical condition. The word “central” refers to the fact that these disorders originate within the central nervous system’s regulation of alertness, rather than being a consequence of poor or fragmented nighttime sleep.
Patients with these conditions often struggle to remain alert during routine activities such as driving, working, or having a conversation. The sleepiness they experience is not relieved by caffeine or willpower, and it may not fully resolve even after sleeping for extended periods. This distinguishes central hypersomnolence disorders from the fatigue associated with a busy schedule or poor sleep habits.
Types of Central Hypersomnolence Disorders
Narcolepsy Type 1
- Sleep paralysis upon waking or falling asleep
- Hypnagogic hallucinations — vivid, dream-like experiences at sleep onset
- Disrupted nighttime sleep despite overwhelming daytime sleepiness
- Automatic behaviors, in which a patient carries out routine tasks with no memory of doing so
Narcolepsy Type 2
Narcolepsy Type 2 presents with the same pattern of excessive daytime sleepiness seen in Type 1, including intrusive sleep episodes that can occur regardless of how much the patient slept the previous night. The key distinction is the absence of cataplexy.
Hypocretin levels are typically normal or only mildly reduced. The condition still significantly impairs daily functioning and requires a formal sleep evaluation — including overnight polysomnography followed by a Multiple Sleep Latency Test (MSLT) — for accurate diagnosis.

Idiopathic Hypersomnia
Idiopathic hypersomnia is characterized by chronic, excessive sleepiness despite sleeping for long periods — often ten or more hours per night. Unlike narcolepsy, patients do not typically experience cataplexy or sudden sleep attacks, but many describe profound sleep inertia upon waking: a prolonged and disabling difficulty achieving full alertness even after an extended sleep.
The term “idiopathic” reflects the fact that no definitive neurological cause has been established, though research into the underlying biology of the condition is ongoing. Idiopathic hypersomnia can be difficult to distinguish from narcolepsy without specialized testing.

Kleine-Levin Syndrome
- Increased appetite, particularly for sweet foods
- Cognitive disturbances, including confusion and difficulty communicating
- Altered perception, with some patients describing a dream-like state
- Behavioral changes, which may include hypersexuality or irritability

Clinical Variables Measured During a Sleep Study
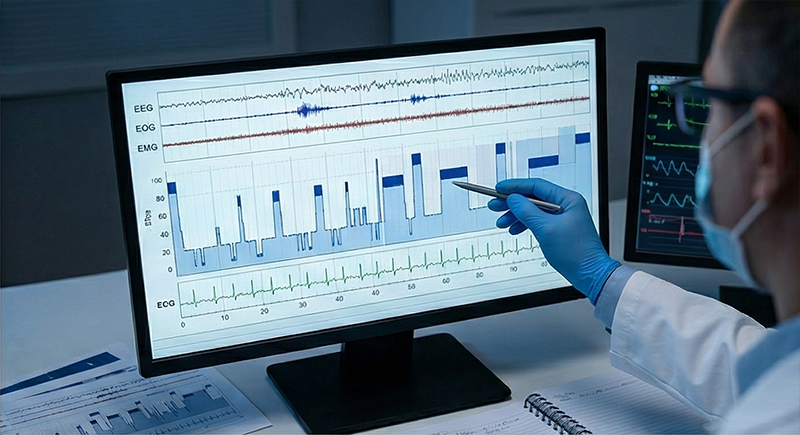
Diagnosing a central hypersomnolence disorder requires ruling out other causes of excessive daytime sleepiness, including obstructive sleep apnea, insufficient sleep, and circadian rhythm disorders. The following variables are evaluated as part of a comprehensive sleep study:
Sleep Architecture (N1, N2, N3, REM)
The distribution of sleep stages across the night. In narcolepsy, REM sleep often appears abnormally early in the sleep cycle — a finding known as a sleep-onset REM period (SOREMP), which is diagnostically significant.
Sleep Latency
The number of minutes it takes to fall asleep. In the Multiple Sleep Latency Test, a mean sleep latency of eight minutes or less across scheduled nap opportunities is a key diagnostic threshold for narcolepsy and idiopathic hypersomnia.
Arousal Index
The number of times per hour the brain briefly activates out of sleep. Reviewed to rule out sleep fragmentation as the underlying cause of daytime sleepiness.
Pulse Oximetry
Continuous monitoring of blood oxygen levels throughout the night to rule out sleep-disordered breathing as a contributor to daytime sleepiness.
Capnography
Measurement of CO2 levels during sleep to assess ventilation and exclude hypoventilation as a contributing factor.
Sleep Hygiene
Behavioral and environmental factors are reviewed to ensure that lifestyle contributors — irregular schedules, insufficient total sleep time, stimulant use — are not a more straightforward explanation for the patient’s sleepiness before a central disorder diagnosis is pursued.
How Hypersomnolence Disorders Are Diagnosed
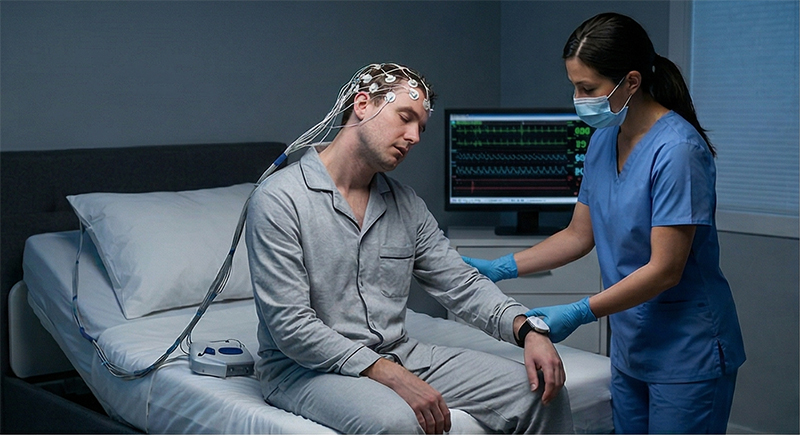
The gold standard for diagnosing central hypersomnolence disorders is a two-part sleep study: an overnight polysomnogram followed the next day by a Multiple Sleep Latency Test (MSLT). During the MSLT, patients are given four to five scheduled 20-minute nap opportunities throughout the day. The time it takes to fall asleep during each nap is recorded, as is the presence of REM sleep.
A mean sleep latency of eight minutes or less, combined with two or more sleep-onset REM periods, is a key diagnostic indicator for narcolepsy. Idiopathic hypersomnia is characterized by short sleep latency without the REM findings.
Prior to testing, patients are typically asked to maintain a consistent sleep schedule and may be asked to discontinue certain medications that could affect results.


“The staff at Becker ENT made me feel comfortable because I was having a little anxiety before the appointment. The staff was very patient with me. My doctor was awesome, and he understood all my issues. Overall, I was satisfied with my care. Thank you so much.”

convenient locations in NJ & PA
Central Disorders of Hypersomnolence Frequently Asked Questions
How is narcolepsy different from simply being very tired all the time?
Narcolepsy involves a neurological disruption in the brain’s ability to regulate sleep and wakefulness — it is not a consequence of insufficient sleep or lifestyle factors. Patients experience intrusive episodes of sleepiness or sleep that occur regardless of how much they slept the night before. The presence of cataplexy, sleep paralysis, or hypnagogic hallucinations alongside persistent daytime sleepiness points strongly toward narcolepsy rather than fatigue related to schedule or habits.
What is cataplexy and how is it recognized?
Cataplexy is a sudden loss of muscle tone triggered by strong emotional experiences, most commonly laughter or surprise. Episodes range from brief facial muscle weakness or a drop in the jaw to a complete fall, all while the patient remains fully conscious. It is one of the defining features of Narcolepsy Type 1 and is not seen in other hypersomnolence disorders. Because episodes can be subtle, patients and families may not immediately recognize them as a medical symptom.
What is the Multiple Sleep Latency Test?
The Multiple Sleep Latency Test (MSLT) is a daytime diagnostic study conducted following an overnight polysomnogram. Over the course of a day, the patient is given four to five scheduled 20-minute opportunities to sleep, and the time it takes to fall asleep during each nap is recorded. The presence of REM sleep during these naps is also noted. Results help quantify the degree of daytime sleepiness and distinguish between narcolepsy types and idiopathic hypersomnia.
Can excessive daytime sleepiness be caused by something other than a central disorder?
Yes. Excessive daytime sleepiness is a symptom shared by several conditions, including obstructive sleep apnea, insufficient sleep, circadian rhythm disorders, and certain medications or medical conditions. A thorough evaluation is necessary to determine the specific cause before a central hypersomnolence disorder is diagnosed. Assuming a diagnosis without proper testing may lead to ineffective or inappropriate treatment.
Is idiopathic hypersomnia the same as feeling groggy in the morning?
No. While many people experience some grogginess upon waking, idiopathic hypersomnia involves a persistent and disabling level of sleepiness that is not relieved by even extended sleep. Patients often describe sleep inertia so severe that they cannot function after waking, and they may remain impaired throughout the day despite sleeping ten or more hours. This level of impairment is distinct from ordinary morning grogginess and warrants clinical evaluation.
What hypersomnolence disorder treatment is near me?
If you live in New Jersey or Pennsylvania, Penn Medicine Becker ENT & Allergy offers evaluation and care for central disorders of hypersomnolence across multiple convenient locations. For a full list of offices, please visit our Locations page.